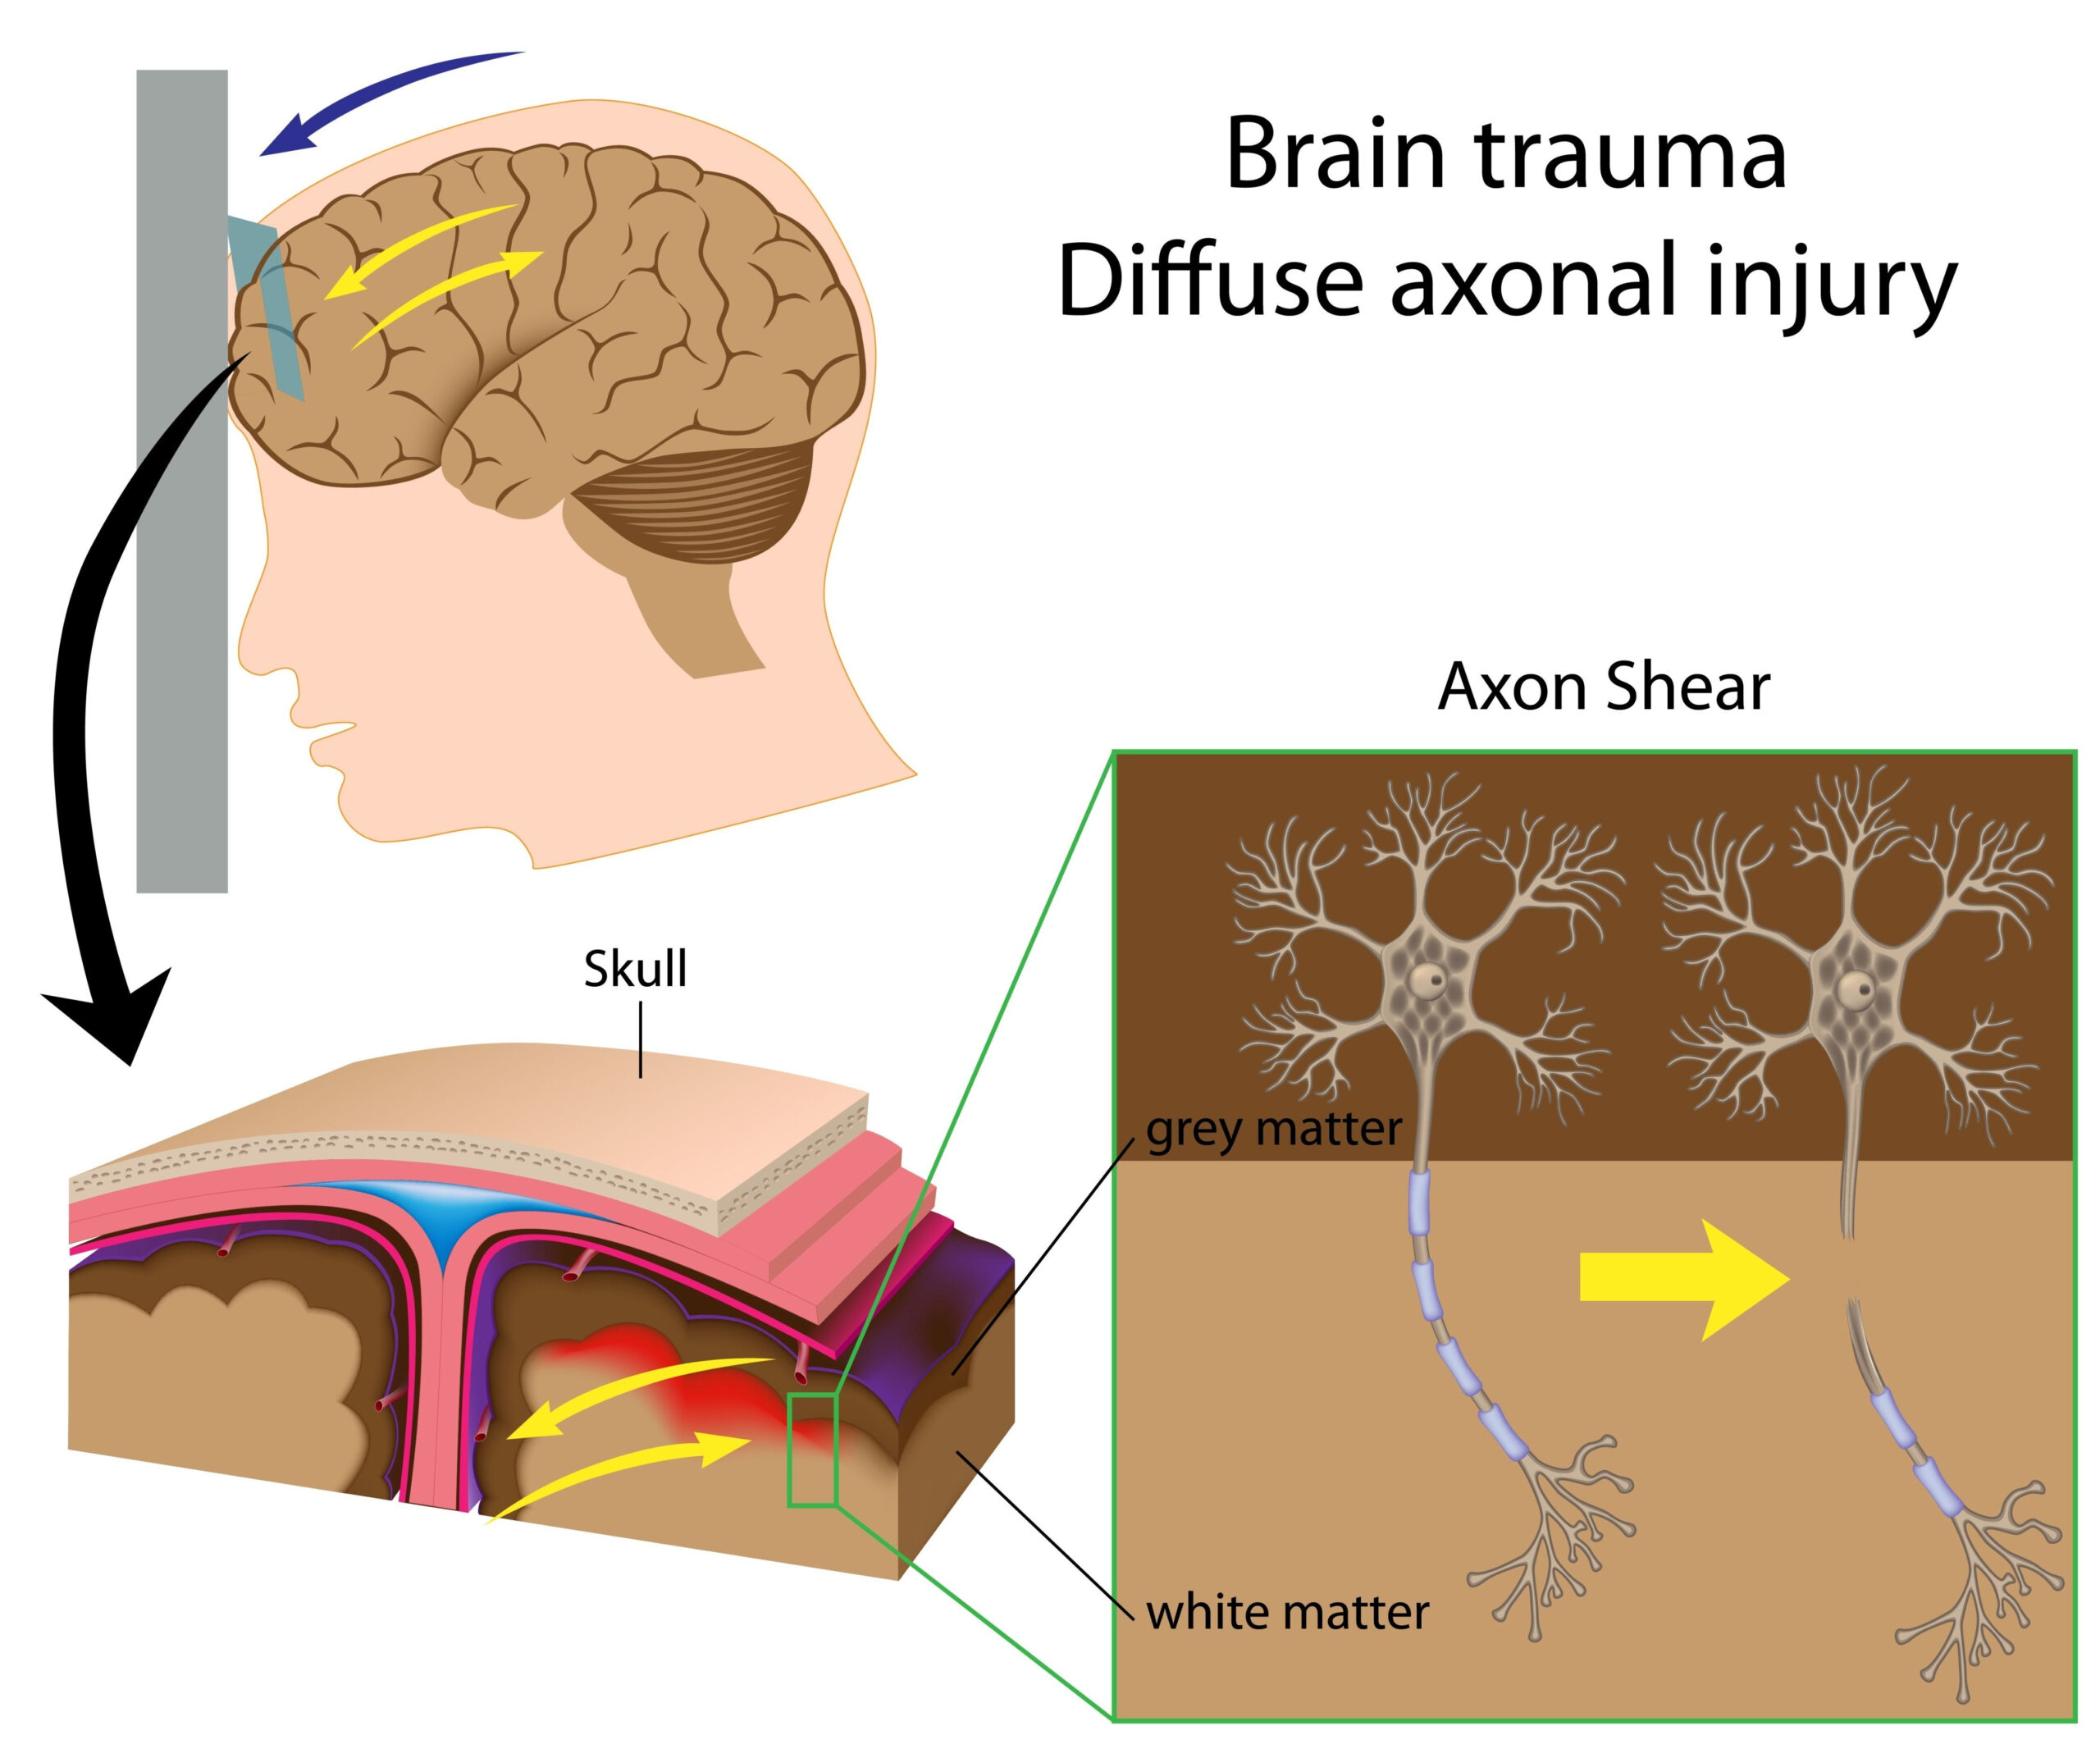
Care Pathway for Mild Traumatic Brain Injury
The management of mild traumatic brain injury (mTBI) begins at the moment of initial contact with emergency services. This pathway is essential in ensuring timely and effective care for patients who have experienced head trauma, particularly in prehospital settings where quick and decisive action is critical.
When a patient presents with potential mTBI after a fall, vehicle accident, or sports-related incident, the first responders typically conduct a focused assessment to evaluate the patient’s level of consciousness, neurological status, and any visible signs of trauma. Utilizing tools like the Glasgow Coma Scale (GCS), responders categorize the severity of the injury, which informs subsequent management decisions. Those scoring between 13 and 15 on the GCS are often considered to have mild injuries, yet they still require careful observation to monitor for any deterioration.
Following the initial evaluation, careful documentation of the mechanism of injury, symptomatology, and vital signs is crucial, as this data informs both immediate care and any future assessments. The patient’s vital signs and history of symptoms—such as headache, dizziness, or confusion—are meticulously recorded, as they can provide insights into the injury’s severity.
In prehospital care, a significant component of the treatment involves patient education. Emergency medical technicians (EMTs) and paramedics often engage with patients and their family members to explain the nature of the injury, potential symptoms to watch for, and when to seek further medical care. This proactive communication not only prepares patients for potential transitions to emergency departments but also empowers them to understand their condition, reducing anxiety.
Transport to an appropriate medical facility is the next step in the care pathway. The decision regarding which hospital to choose can depend on several factors including proximity, available resources, and whether the facility has a designated trauma center. While severe cases may warrant immediate transfer to specialized centers, mild cases may be diverted to other facilities better suited for managing outpatient care.
Within the hospital setting, a comprehensive evaluation continues. This may include advanced imaging techniques such as CT scans to eliminate the possibility of more severe intracranial injuries. However, in line with current clinical guidelines, many patients with mTBI may not require imaging if their symptoms are stable and they possess a favorable clinical history.
Following assessment, treatment plans often focus on symptom management, which can range from analgesics for headaches to guidance on rest and activity modification. Follow-up care is imperative to monitor recovery progress, and patients often receive instructions on recognizing signs that require urgent re-evaluation.
In summary, the care pathway for mTBI in prehospital emergency services is a multi-step process that prioritizes rapid assessment, education, and safe transport to appropriate medical facilities, while also ensuring ongoing support and guidance for recovery. This pathway not only seeks to mitigate immediate risks but also aims at their long-term recovery and rehabilitation.
Current Practices in Prehospital Care
In the realm of prehospital care for mild traumatic brain injury (mTBI), emergency medical services (EMS) play a pivotal role in bridging immediate response and subsequent medical treatment. A tailored approach in these settings is essential for optimizing patient outcomes.
Upon arriving at the scene, EMS personnel typically initiate the care process by maximizing safety and minimizing further risk to the patient. They assess critical aspects such as the patient’s environment and the mechanism of injury. This initial assessment is comprehensive. It includes not only a neurological examination but also a systematic evaluation of the patient’s airway, breathing, and circulation, which is essential in any trauma case.
The use of screening tools remains central to this initial evaluation. The Glasgow Coma Scale (GCS) is widely adopted, providing a standardized method to categorize levels of consciousness and focus the EMS team’s subsequent decisions. A GCS score in the range of 13-15 indicates a mild injury but necessitates vigilance, as subtle changes in consciousness can herald a decline in the patient’s condition.
Importantly, the documentation of findings during this initial evaluation is vital. EMS providers meticulously record vital signs, the specific nuances of the mechanism of injury, and any neurological deficits observed. This detailed documentation is invaluable to healthcare providers in the emergency department, as it forms the foundation for continued management and allows for a more informed decision-making process upon patient handoff.
Patient education represents another critical component of prehospital care. Emergency responders engage patients and their families by elucidating the nature of mTBI, discussing potential symptoms that may arise, and setting clear expectations for follow-up care. This interaction can alleviate patient anxiety and provides a support system that aids understanding of their condition. Responders often advise patients on when to seek further medical attention, emphasizing the importance of awareness of any new or worsening symptoms.
Transport logistics of the patient are carefully considered, influencing the choice of medical facility. Proximity to a hospital is often a key factor, but the specific capabilities of the facility can dictate transport decisions as well. While some patients may need urgent transfer to a trauma center for specialized care, many with mTBI can be appropriately treated at facilities equipped for outpatient management.
In the hospital setting, the approach to care continues seamlessly from prehospital assessments. For patients with mTBI who present to emergency departments, thorough evaluations—including potential imaging studies such as CT scans—are conducted when clinically indicated. Current guidelines suggest a cautious approach to imaging in mild cases, preventing unnecessary radiation exposure while ensuring that more severe intracranial injuries are not overlooked.
Post-assessment, the focus shifts to symptomatic treatment and supportive care, which may include recommendations for rest, physical activity management, and analgesics for headache relief. Ensuring a clear follow-up plan is essential, as ongoing assessment of recovery can identify any complications early. Instructions provided to patients emphasize recognizing warning signs, thereby fostering an active role in their recovery process.
Overall, current practices in prehospital care involve a careful blend of assessment, documentation, patient education, and logistical decisions. These efforts synergistically aim to ensure effective response to mTBI while laying the groundwork for successful patient recovery in subsequent care settings.
Potential of Point-of-Care Biomarkers
The emergence of point-of-care biomarkers holds substantial promise for enhancing the management of mild traumatic brain injury (mTBI) in prehospital settings. Biomarkers are measurable indicators found in bodily fluids that can provide vital information regarding the presence and severity of brain injuries. These emerging technologies could revolutionize the approach to diagnosing mTBI, especially in a prehospital context where quick decisions are paramount.
One of the primary advantages of point-of-care biomarkers is their ability to deliver rapid results, often within minutes. Traditional diagnostic methods, such as neuroimaging, can be time-consuming and resource-intensive, potentially delaying treatment. In contrast, nearby detection and analysis of biomarkers could enable emergency medical services (EMS) personnel to make more informed decisions regarding patient management and transport. For instance, specific biomarkers associated with neuronal damage, such as S100B protein and glial fibrillary acid protein (GFAP), have shown promise in clinical trials. Elevated levels of these biomarkers can correlate with brain injury severity, allowing for risk stratification of patients in the field.
Additionally, incorporating point-of-care testing into the prehospital setting can improve patient flow through emergency departments by mitigating unnecessary transport of patients who might be well-managed outside acute care facilities. With the aid of biomarkers, EMS teams could more accurately assess which patients require advanced imaging or observation, potentially reducing hospital overcrowding and enhancing overall efficiency in trauma care.
Moreover, the use of point-of-care biomarkers may facilitate better patient education and engagement. Emergency responders can explain to patients and their families the rationale behind biomarker testing, which may empower patients and help reduce anxiety about their situation. Understanding the implications of biochemistry behind their injuries gives patients greater insight into their condition, fostering a partnership in recovery.
Current challenges to the implementation of point-of-care biomarkers include the need for robust validation within diverse populations and conditions. Biomarkers must be proven effective across various demographics and within different contexts to gain acceptance within clinical guidelines. Furthermore, EMS personnel must receive appropriate training to interpret biomarker results effectively and integrate these into their existing protocols.
Researchers are actively exploring various aspects of biomarker use in relation to mTBI. Investigating new biomarker candidates and assessing their functional capabilities in real-world scenarios will be pivotal. Future research should focus on the long-term effects of utilizing these biomarkers, evaluating outcomes related to clinical decision-making and patient prognosis. Prospective studies examining the efficacy of point-of-care testing compared to traditional methods would be invaluable in determining its role in the management of mTBI.
In summary, the potential of point-of-care biomarkers in the prehospital management of mild traumatic brain injuries is vast. By delivering rapid, actionable results and enhancing clinical decision-making, these biomarkers could significantly transform the landscape of emergency care, ultimately leading to improved patient outcomes. The ongoing research in this area is crucial for ensuring that point-of-care solutions are not only scientifically sound but also effectively integrated into everyday practice within EMS frameworks.
Recommendations for Future Research
The advancement of care pathways for mild traumatic brain injury (mTBI) relies heavily on rigorous scientific inquiry. Future research should prioritize several key areas to enhance understanding, diagnostic capabilities, and treatment methodologies associated with mTBI.
One critical avenue is the exploration of novel biomarkers and their integration into clinical practice. The identification of new, reliable point-of-care biomarkers could significantly improve diagnostic accuracy during prehospital assessments. Studies should focus on validating existing biomarkers like S100B and GFAP across diverse populations and injury contexts. This involves assessing their predictive value for outcomes in mild brain injuries and refining protocols to ensure they are effective across various demographics. Rigorous multicenter trials are essential to establish consensus on which biomarkers should be adopted into standard practice for EMS.
Additionally, research should delve into the training requirements for EMS personnel regarding the interpretation of biomarker data. Comprehensive educational programs need to be developed, enabling first responders to make informed clinical decisions based on biomarker results. Evaluating the impact of this training on clinical outcomes will provide insights into potential improvements in patient care.
Another significant research area involves the comparison of point-of-care biomarker testing to traditional imaging modalities like CT scans. Investigating the efficacy and cost-effectiveness of these approaches will help in establishing a more streamlined protocol for mTBI assessment. Randomized control trials could elucidate whether the use of biomarkers could effectively reduce unnecessary imaging, thereby minimizing radiation exposure for patients and optimizing resource allocation in emergency departments.
The long-term effects and trajectories of patients diagnosed with mTBI also warrant further examination. Large-scale longitudinal studies could provide valuable insights into symptom progression and outcomes associated with initial prehospital assessments. Understanding the natural history of mTBI, including factors influencing recovery such as age, prior head injuries, and comorbid conditions, will enhance both the management strategies in acute care and the development of appropriate educational resources for patients.
Collaboration between researchers, healthcare professionals, and policymakers is essential to translate knowledge into practice effectively. Research efforts should also focus on creating comprehensive guidelines that incorporate new findings into existing frameworks. This includes addressing the potential barriers to the implementation of biomarker testing, such as financial costs, resource availability, and differences in regional care capabilities.
Moreover, the experiences and perspectives of patients who suffer from mTBI should be an integral part of future research. Engaging patients in studies concerning their recovery journey can reveal critical insights into perceived challenges, emotional impacts, and the efficacy of educational initiatives. Qualitative research methods can be particularly valuable in capturing these nuanced experiences, ultimately guiding better patient-centered approaches in care.
In conclusion, the path forward for research in the field of mild traumatic brain injury is multifaceted. By focusing on the enhancement of biomarker usage, ongoing training for EMS personnel, comparisons with traditional diagnostic methods, long-term outcome studies, and integrating patient perspectives, future research can significantly bolster the management of mTBI, translating to improved outcomes for affected individuals.