Symptoms of Autonomic Dysfunction
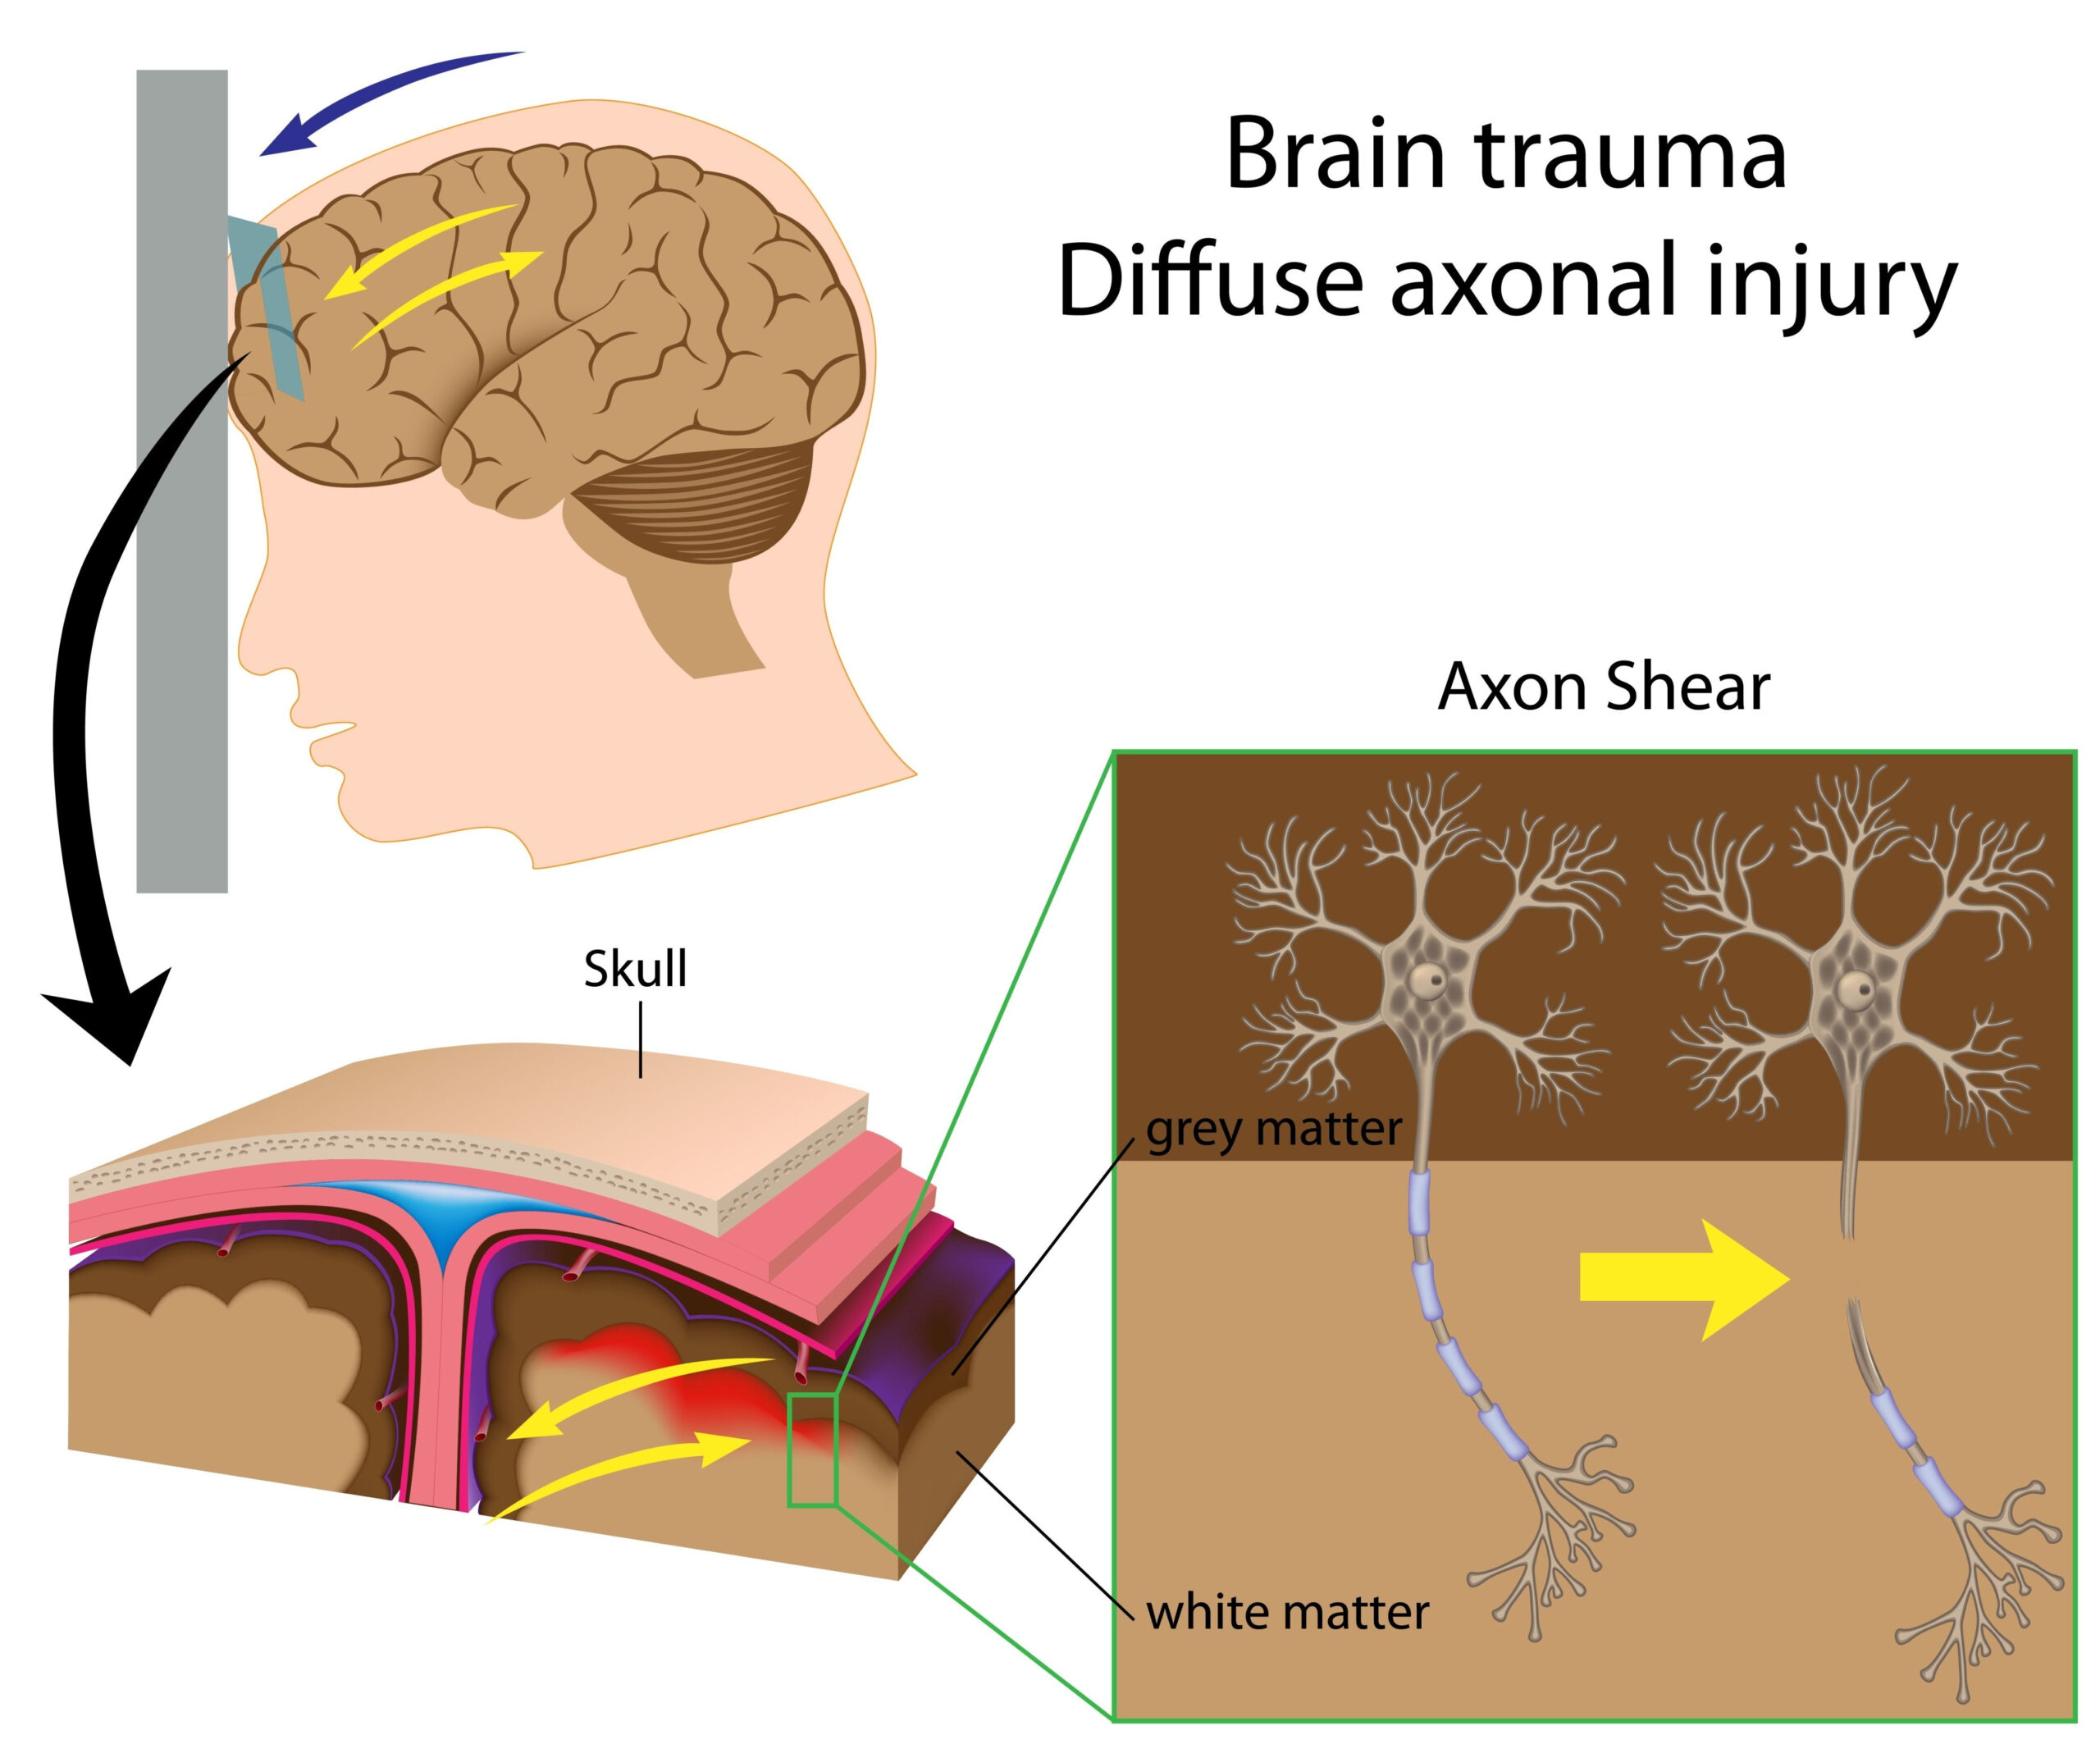
Autonomic dysfunction encompasses a range of symptoms that emerge when the autonomic nervous system (ANS) is compromised. This system is integral to regulating involuntary bodily functions, such as heart rate, blood pressure, digestion, and temperature control. Individuals experiencing acute post-traumatic headache (PTH) due to mild traumatic brain injury (mTBI) often report a variety of symptoms consistent with autonomic irregularities.
Common manifestations of autonomic dysfunction can include cardiovascular symptoms such as orthostatic hypotension, where an individual experiences a significant drop in blood pressure upon standing, leading to dizziness or fainting. Heart rate variability may also be affected, resulting in either tachycardia or bradycardia, which could contribute to feelings of palpitations or increased anxiety.
Gastrointestinal disturbances are frequently noted in patients with autonomic dysfunction, often presenting as nausea, bloating, or altered bowel habits. This gastrointestinal involvement can stem from the ANS’s role in regulating gut motility and secretions, revealing how intertwined these symptoms are with the overall autonomic response.
Additionally, temperature regulation may become disrupted, resulting in excessive sweating or an inability to tolerate temperature changes. Patients might report unusual heat sensitivity or cold extremities, which can significantly diminish their quality of life. These symptoms can also lead to considerable discomfort, further compounding the challenges faced by individuals recovering from mTBI.
Other reported symptoms include sleep disturbances, such as insomnia or excessive daytime sleepiness, which are part of a broader pattern of fatigue and lack of energy. These issues may arise from the interplay between pain perception, mood disorders, and autonomic responses to stress.
Importantly, the presence and severity of these autonomic symptoms can vary greatly among individuals, underscoring the need for tailored evaluations and interventions. The impact of autonomic dysfunction on overall recovery from acute post-traumatic headache remains an essential area of research, particularly as these symptoms can overlap with other post-concussion phenomena.
Study Design and Participants
This study employed a cross-sectional design to evaluate the prevalence and nature of autonomic dysfunction in individuals experiencing acute post-traumatic headache following mild traumatic brain injury. Participants were recruited from a specialized clinic focused on concussion management, ensuring that the cohort consisted of individuals who met defined inclusion criteria for mTBI. These criteria included a documented history of head trauma, a subsequent diagnosis of concussion, and the presence of headache symptoms that developed within the acute phase post-injury, typically within the first week.
The study aimed to include a diverse sample encompassing various demographic backgrounds, with participants aged 18 to 65. Exclusion criteria were established to eliminate confounding factors; individuals with a history of neurological disorders, previous autonomic dysfunction, or ongoing psychiatric conditions were not included in the study to ensure that observed symptoms were primarily attributed to the recent brain injury and not other underlying issues.
To assess autonomic function, a series of standardized tests were administered, including heart rate variability (HRV) assessment and the passive stand test, which evaluates orthostatic response. Participants underwent measuring procedures under controlled conditions—resting heart rates and blood pressure levels were recorded before and after standing, allowing for accurate assessment of their autonomic responses upon postural changes.
In addition, subjective symptom questionnaires were utilized, enabling participants to report their experiences related to gastrointestinal disturbances, sleep issues, and overall quality of life. These self-reported measures were critical for capturing the multifaceted nature of symptoms experienced by individuals following mTBI and were analyzed alongside objective data to provide a comprehensive understanding of autonomic dysfunction in this context.
Following recruitment and data collection, participants were categorized based on their symptom profiles, allowing researchers to explore correlations between the severity of autonomic symptoms and other factors, such as the duration of headaches and general recovery trajectories. This stratification ultimately aimed to inform potential treatment approaches tailored to the individual needs of those affected by acute post-traumatic headache and autonomic dysfunction.
Results and Analysis
The analysis of data gathered from participants revealed significant insights into the prevalence and impact of autonomic dysfunction among individuals suffering from acute post-traumatic headache due to mild traumatic brain injury. Among the cohort, a notable proportion exhibited demonstrable signs of autonomic dysregulation, as indicated by clinical evaluations and self-reported symptoms. Heart rate variability assessments and postural change tests provided objective metrics that complemented participants’ subjective experiences.
Statistical analysis highlighted a clear association between autonomic symptoms and the severity and duration of headaches, suggesting that those with pronounced autonomic dysfunction tended to report more intense headache experiences. For instance, participants who displayed significant heart rate deviations during the passive stand test were also more likely to describe their headaches as debilitating, with additional symptoms such as dizziness and fatigue complicating their recovery.
Furthermore, gastrointestinal symptoms emerged as a common complaint within this population. The prevalence of nausea and altered bowel habits were prevalent, with nearly half of the participants noting these symptoms as significant burdens that affected their daily functioning. The integration of gastrointestinal questionnaires allowed for a focused examination of how these symptoms correlated with autonomic issues, reinforcing the understanding that the ANS’s influence extends far beyond cardiovascular responses.
Another critical finding involved temperature regulation difficulties. Participants frequently reported issues such as excessive sweating and cold intolerance, which not only contributed to physical discomfort but also negatively impacted their emotional well-being. The qualitative data gathered from self-reports shed light on the psychological ramifications of these physical symptoms, linking them to increased anxiety and mood fluctuations that could hinder the recovery journey.
Furthermore, sleep quality assessments indicated that disturbances were significantly more common among those exhibiting autonomic dysfunction. Individuals with marked autonomic symptoms reported higher instances of insomnia and feelings of exhaustion during the day. This interplay between autonomic dysfunction and sleep patterns poses questions about how effectively managing autonomic symptoms might improve overall health outcomes.
In essence, the results elucidate a complex interrelationship between various autonomic symptoms and the experience of acute post-traumatic headache. This analysis underscores the necessity for clinicians to consider not only the headache itself but also the broader spectrum of autonomic dysfunction that patients may encounter. The insights gained from this study lay the groundwork for future interventions aimed at improving comprehensive care strategies for those affected by mTBI and its associated challenges.
Future Research Directions
The findings of the current study highlight the critical relationship between autonomic dysfunction and acute post-traumatic headache (PTH) in the context of mild traumatic brain injury (mTBI). To build upon these insights, several avenues for future research emerge, each aimed at refining our understanding and management of these complex interactions.
One area ripe for exploration involves longitudinal studies that track the progress of autonomic symptoms over time following an mTBI. By extending the timeline of inquiry beyond the acute phase, researchers could discern how autonomic dysfunction evolves, potentially identifying markers that predict long-term recovery trajectories. This would enhance the clinical management of individuals with a history of mTBI, allowing healthcare providers to implement interventions tailored to their evolving needs.
Another promising direction lies in the investigation of specific treatment modalities aimed at mitigating autonomic dysfunction symptoms. Randomized controlled trials evaluating pharmacological treatments, neurostimulation techniques, and lifestyle interventions could provide valuable evidence regarding effective strategies. For instance, examining how beta-blockers may alleviate symptoms of tachycardia or exploring behavioral therapies to address gastrointestinal disturbances could yield practical approaches to improve patient quality of life.
Additionally, research into the mechanisms underlying these autonomic disturbances is key. Understanding the pathophysiological changes that occur post-injury could unveil critical targets for therapeutic interventions. Biomarkers indicating autonomic dysfunction could be explored as potential diagnostic tools, enabling more precise identification of patients at risk for severe symptoms early in their recovery phase.
Furthermore, the relationship between sleep disturbances and autonomic dysfunction warrants further examination. Given the significant association noted in this study, future investigations could assess the impact of sleep interventions on overall autonomic functioning. Interventions such as cognitive-behavioral therapy for insomnia or mindfulness practices have shown promise in other contexts and could be evaluated for their effectiveness in patients recovering from mTBI.
Lastly, expanding the demographic breadth of research participants will be crucial to understanding the effects of autonomic dysfunction across various populations. Factors such as age, sex, and comorbidities could influence symptom expression and recovery outcomes. By including a diverse cohort, researchers can ascertain whether specific subgroups experience unique challenges, enabling the development of targeted strategies that respect these differences.
As we advance our comprehension of autonomic dysfunction in the aftermath of mild traumatic brain injury, a multidisciplinary approach—incorporating neurology, psychology, and rehabilitation sciences—will be essential. This integrative framework will not only enhance patient care but also promote holistic understanding, ultimately fostering better health outcomes for those affected by acute post-traumatic headache.